Category: Medical

Upper Gastrointestinal Bleed (UGIB)

Not normally difficult to spot, but look for it in unexplained anaemia, or collapse.

Questions

  • Is it VARICEAL? Mortality 35%, so is an emergency whatever the GBS is.
  • Non-Variceal what’s the GBS? will help guide treatment

Anyone being admitted should be brought to HRI

Emergency Endoscopy is arranged by Med Reg

Read more

Rabies [notifiable disease]

Recent Incident: Bat contact was not recognised (effectively touching a bat without gloves means treatment is recommended)

Important: Rabies Vaccine is in short supply and we must do a UKHSA risk assessment.  Call RIgS 09:30-17:00 7 days, Info required HERE


Rabies is an acute viral encephalomyelitis caused by members of the lyssavirus genus. The UK has been declared “Rabies-Free”. However, it is known that even in  “Rabies-Free” counties the bat population posse a risk.

In the UK the only bat to carry rabies is the Daubenton’s Bat [Picture on the Left] and this is not a common bat in the UK. The UK and Ireland are Classified as “low-risk” for bat exposure. Despite our “low-risk” status in 2002 a man died from rabies caught in the UK from bat exposure.

Although rabies is rare it is fatal so we must treat appropriately, Public Health England – Green book details this.

Risk Assessment

To establish patients risk and thus treatment you need to establish the Exposure Category and Country Risk [Link to Country Risk]

Exposure Category

Combined Country/Animal & Exposure Risk
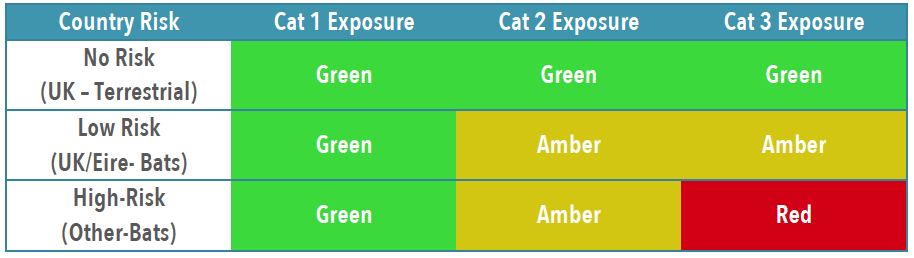
Treatment

Obviously patients with wounds will need appropriate wound care and cleaning, specifics for rabies are below.

If in ANY doubt, or you feel you need advice about treatment contact: On-Call Microbiologist (who will contact PHE or Virology advice)


You will likely need to liaise with the duty pharmacist to obtain vaccine or HRIG – which may need to be sent from a different hospital. [it is probably worth trying to obtain the 1st weeks treatment if possible, to avoid treatment delays]

IN HOURS 08:30AM-5PM PLEASE CALL PHARMACY TO INFORM THEM TO EXPECT A DELIVERY OF IMMUNOGLOBULIN SO THIS CAN BE SEGREGATED FOR THE CORRECT PATIENT. PLEASE ASK TO SPEAK TO THE RESPONSIBLE PHARMACIST                      CRH (4218/4279) HRI (2422/7123) 


UKHSA Rabies and Immunoglobulin Service (RIgS)

  • Telephone: 0330 128 1020

Routine operating hours: 09:30–17:00, seven days per week, including weekends.

All patients presenting with a possible rabies exposure should undergo an initial clinical assessment, including wound management, assessment of the exposure and previous vaccination history.

During routine hours: Contact RIgS for specialist risk assessment, advice on post-exposure vaccination and any requirement for human rabies immunoglobulin (HRIG).

Outside routine hours:

  • For the highest-risk exposures in patients who have not received their first post-exposure vaccine dose, contact the UKHSA emergency duty doctor service. These include head or neck exposures (excluding UK bat exposures under this specific criterion) and exposure to an animal confirmed to have rabies.
  • For other potential rabies exposures, administer a dose of rabies vaccine if the patient has not yet received vaccine, or if a scheduled dose is due, provided vaccine is available locally.
  • Contact RIgS after 09:30 the following day to complete the risk assessment and confirm further treatment.

All advice and administered treatment must be documented in the patient’s clinical record. Pharmacy must be informed of vaccine and HRIG administration, and arrangements made for subsequent doses.

HRIG: Indications, dosage and administration must follow the current UKHSA interim recommendations for HRIG use (June 2025), alongside the national rabies post-exposure treatment guidance.

Information required for next morning referral – HERE


Mitochondrial Disease

Mitochondrial diseases are a diverse group of inherited disorders characterised by dysfunction of the mitochondrial respiratory chain, resulting in impaired cellular energy production.

These conditions frequently affect multiple organ systems and can present significant challenges in the Emergency Department. Evidence to guide management remains limited, particularly for specific complications, and specialist advice is often required.

Key principles for emergency care:

Mitochondrial Disease Information

Access specialist NHS information about mitochondrial diseases, including clinical features, diagnosis and management.

View NHS Mitochondrial Disease Info

Clinical Care Guidelines

Access specialist NHS guidance for healthcare professionals on the assessment, management and ongoing care of patients with mitochondrial disease.

View NHS Clinical Care Guidelines

Hyperkalaemia

Remember: is it a haemolysed blood sample? (you can do an iSTAT)

Severity

  • Mild: 5.5-5.9mmol/l – No urgent action required (Dietary & Medication modification & GP F/U)
  • Moderate: 6.0-6.4mmol/l – Follow treatment guide (maybe suitable for discharge)
  • Severe: ≥6.5mmol/l OR ECG changes – Follow treatment guide, must admit

Read more

Myocardial Infarction (MI) – PPCI/Thrombolysis

PPCI

Target:
Door to balloon 90min

Criteria Time:
Chest pain within 12hrs (or worsened within 12hrs)

ECG: 
ST elevation MI (2 contiguous: 1mm Limb or 2mm Chest leads)
New LBBB.
(Posterior MI do posterior leads and discuss with LGI)

Actions:
Resuscitate as required
Contact PPCI team @ LGI (Mobile No. up in Resus)
Arrange blue light (P1) ambulance to LGI

Medication:
Prasagrel 60mg if – no previous CVA
Ticagrelor 180mg if previous CVA and Aspirin 300mg
Anti-coagulated Discuss with PPCI team

PPCI – POSTER

Read more

End of life care in the Emergency Department

Why recognising dying matters

Recognising that someone may be approaching the end of their life can be difficult, particularly in the busy and sometimes unpredictable environment of the Emergency Department. We may meet people and families at a moment of profound distress, with little time to build a relationship or understand what matters most to them. It is understandable that these conversations feel daunting.

Yet recognising the possibility of dying creates an opportunity to offer the right care: to treat distress, consider reversible problems, explain uncertainty honestly and help patients and those close to them make informed choices. End of life care is not an alternative to good emergency medicine; it is part of it. Compassionate care remains active care.

Read more

Atrial Fibrillation/Flutter

Actions

It’s essential any Modifiable causes are treated, these include:

    • Haemodynamic stress: Valvular disease/Hypertension/LVD/Thrombus
    • Atrial ischemia: Ischaemic Heart Disease
    • Inflammation: Sepsis/Myocarditis/pericarditis
    • Noncardiovascular respiratory causes: PE/Pneumonia/Lung Cancer
    • Alcohol and drug use: Alcohol/Cocaine/Amphetamine
    • Endocrine disorders: Hyperthyroid/Diabetes/Phaeochromacytoma/Electrolyte prob.
    • Neurologic disorders: Subarachnoid Haemorrhage/Stroke
    • Genetic factors
    • Advancing age

Tests (NEW AF)

  • 12 Lead ECG
  • Bloods: FBC, U&E, Bone profile, Magnesium, LFT, TFT, Clotting, Glucose
  • Others: individualised to the patient.
  • First line:
    • β-Blocker – outperforms calcium channel blockers in studies
    • Non-dihydropyridine calcium channel blockers (Diltiazem/Verapamil) – esp. in Severe COPD/Asthma
  • Second Line:Consider adding in
    • Digoxin – however, digoxin alone is not effective in patients with increased sympathetic drive. Observational studies have associated digoxin use with excess mortality in AF patients)
    • Amiodarone can be useful as a last resort when heart rate cannot be controlled with combination therapy in patients who do not qualify for non-pharmacological rate control

Rhythm control in ED

“Early cardioversion is not recommended without appropriate anticoagulation or transoesophageal echocardiography if AF duration is longer than 24 h, or there is scope to wait for spontaneous cardioversion.”

In reality risks increase beyond 12hrs from onset, and those reverted in ED will often return to AF by the time they get to AF clinic follow up.

  • ESC/NICE recommends using the CHADS-VASc to assess stroke risk and ORBIT to assess bleeding risk
  • There are currently significant delays getting to “New AF” clinic as well as to GP’s, making assessment of Stroke risk in ED more important than ever

CHADS-VASc outcome recommendations

    • Males (0), Female (1) – No anticoagulation recommended
    • Males (1) – Consider anticoagulation (DOAC) in light of bleed risk
    • ALL (≥2) – Anticoagulation recommended (DOAC)- Trust DOAC guide,  NICE/CKS
    • Use Apixaban where first line, significantly cheaper. If using alternative please document reasons.

ORBIT outcome recommendations

    • Modifiable risks – Address ALL modifiable risk factors
    • Most will benefit from anticoagulation – but discuss personalised risk with patients

Contraindications to Anticoagulation inc:

    • Active serious bleeding (where the source should be identified and treated)
    • Associated comorbidities (e.g. severe thrombocytopenia <50 platelets/lL, severe anaemia under investigation, etc.)
    • Recent high-risk bleeding event such as intracranial haemorrhage (ICH).
  • Life Style
    • Obesity: Risk of AF, Recurrence of AF and Stoke all increase with BMI
    • Alcohol: Alcohol excess both increases the risk of AF and of Bleeding, so patient should support to reduce aldol intake is recommended
    • Caffeine: It is unlikely caffeine consumption causes AF. Habitual caffeine use may reduce the risk of developing AF. But increases the symptoms
    • Exercise: Moderate cardiavasclar exercise is protective, however higher rates of AF are seen in elite athletes and vigorous physical activity
  • Specific conditions- patient should follow up with GP/Clinic (treatment may start in ED)
    • Hypertension
    • Heart Failure
    • Coronary artery disease
    • Diabetes Mellitus
    • Sleep Apnoea

Arrhythmia clinic is for patients with newly diagnosed and symptomatic AF/SVT (if the patient is not symptomatic they should be followed up through their GP).

It should be remembered that patients will be seen after at least 6 weeks so anticoagulation decisions should not be delayed for clinic.

GUIDANCE

Based primarily on:

EMbeds clinical quick guide

Last evidence review: October 2026
Suggested next review: October 2026

This is a clinical support guide and does not replace clinical judgement, current CHFT medicines guidance or specialist advice.

Anaphylaxis 2021

Not all Allergies are Anaphylaxis!

Anaphylaxis is defined as:

  • Severe life-threatening systemic hypersensitivity reaction
  • Where BOTH of the following criteria are met:
    1. Sudden onset & rapid progression
    2. Life-threatening compromise of ONE or MORE of: Airway/Breathing/Circulation

Read more

Acute Coronary Syndrome (ACS) – 2025

First take a good history, not ALL chest pain needs to be investigated as ACS. However, its worth noting older patients and women are more likely to have atypical presentations. Be wary that some patients with negative troponin give a history of Unstable Angina and therefore require admission.

Read more: Acute Coronary Syndrome (ACS) – 2025

ACS Treatment (Not STEMI going for PPCI)

  • Aspirin 300mg stat
  • Ticagrelor 180mg stat
  • Fondaparinux 2.5mg sc stat. 

Anticoagulated with a DOAC, or with Warfarin (with a therapeutic INR),

  • Aspirin 300mg stat
  • Clopidogrel 300mg stat

ACS &Aspirin Allergy

  • If the history suggests intolerance (GI upset, dyspepsia, nausea etc) rather than allergy, aspirin rechallenge is justifiable.
  • In TRUE allergy aspirin should be avoided. > Give Ticagrelor 180mg + Fondaparinux 2.5mg (unless contraindicated)
  • Any doubts contact Cardiology on-call Con
  • Aspirin 300mg stat
  • Plus Either:
    • Ticagrelor 180mg stat (Hx of CVA)
    • Prasugrel 60mg stat (NO Hx of CVA)

Direct admissions to CCU

Patients with ST Elevation (if not accepted for primary PCI) or those with CP + new ST Depression should be discussed with a local Cardiologist and come directly to CCU.

As it is difficult to be prescriptive for every other circumstance, a discussion with a senior/cardiologist may be worthwhile in order to best manage and place your patient within the hospital.

Patients where MI is excluded

If patients do exit the pathway (no new symptoms, no new ECG ischemia and troponins that meet the exit criteria to exclude an MI), two other important possibilities still require consideration:

  1. Is the history in keeping with unstable angina? (This is still an ACS). If so the patient will require an acute inpatient admission with telemetry and IP cardiology review.
  2. Is the chest pain due to a significant alternative diagnosis? If so this still needs to be actively considered/ investigated/ treated.
