Recent Incident: Bat contact was not recognised (effectively touching a bat without gloves means treatment is recommended)
Important: Rabies Vaccine is in short supply and we must do a UKHSA risk assessment. Call RIgS 09:30-17:00 7 days, Info required HERE

Rabies is an acute viral encephalomyelitis caused by members of the lyssavirus genus. The UK has been declared “Rabies-Free”. However, it is known that even in “Rabies-Free” counties the bat population posse a risk.
In the UK the only bat to carry rabies is the Daubenton’s Bat [Picture on the Left] and this is not a common bat in the UK. The UK and Ireland are Classified as “low-risk” for bat exposure. Despite our “low-risk” status in 2002 a man died from rabies caught in the UK from bat exposure.
Although rabies is rare it is fatal so we must treat appropriately, Public Health England – Green book details this.
Risk Assessment
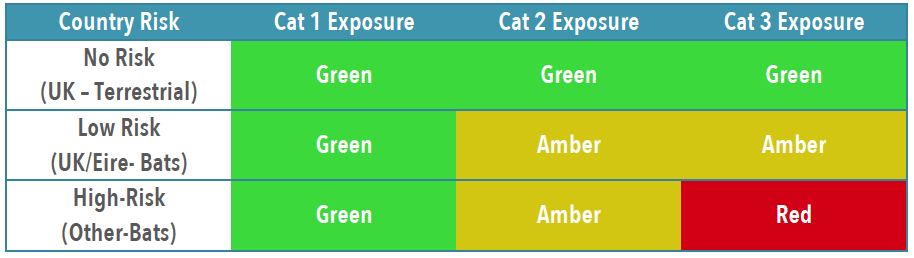
To establish patients risk and thus treatment you need to establish the Exposure Category and Country Risk [Link to Country Risk]
Exposure Category

Combined Country/Animal & Exposure Risk
Treatment
Obviously patients with wounds will need appropriate wound care and cleaning, specifics for rabies are below.
If in ANY doubt, or you feel you need advice about treatment contact: On-Call Microbiologist (who will contact PHE or Virology advice)

You will likely need to liaise with the duty pharmacist to obtain vaccine or HRIG – which may need to be sent from a different hospital. [it is probably worth trying to obtain the 1st weeks treatment if possible, to avoid treatment delays]
IN HOURS 08:30AM-5PM PLEASE CALL PHARMACY TO INFORM THEM TO EXPECT A DELIVERY OF IMMUNOGLOBULIN SO THIS CAN BE SEGREGATED FOR THE CORRECT PATIENT. PLEASE ASK TO SPEAK TO THE RESPONSIBLE PHARMACIST CRH (4218/4279) HRI (2422/7123)
UKHSA Rabies and Immunoglobulin Service (RIgS)
- Telephone: 0330 128 1020
Routine operating hours: 09:30–17:00, seven days per week, including weekends.
All patients presenting with a possible rabies exposure should undergo an initial clinical assessment, including wound management, assessment of the exposure and previous vaccination history.
During routine hours: Contact RIgS for specialist risk assessment, advice on post-exposure vaccination and any requirement for human rabies immunoglobulin (HRIG).
Outside routine hours:
- For the highest-risk exposures in patients who have not received their first post-exposure vaccine dose, contact the UKHSA emergency duty doctor service. These include head or neck exposures (excluding UK bat exposures under this specific criterion) and exposure to an animal confirmed to have rabies.
- For other potential rabies exposures, administer a dose of rabies vaccine if the patient has not yet received vaccine, or if a scheduled dose is due, provided vaccine is available locally.
- Contact RIgS after 09:30 the following day to complete the risk assessment and confirm further treatment.
All advice and administered treatment must be documented in the patient’s clinical record. Pharmacy must be informed of vaccine and HRIG administration, and arrangements made for subsequent doses.
HRIG: Indications, dosage and administration must follow the current UKHSA interim recommendations for HRIG use (June 2025), alongside the national rabies post-exposure treatment guidance.
Information required for next morning referral – HERE


 the iNFANT is truly a design enigma, it is simple yet complicated, amazing yet frustrating, beautiful yet disgusting. And due to a unique production method, each iNFANT has its own variations and special features.
