- Keep your suspicions high – early signs it may not be clear
- Sepsis Kills – give antibiotics & fluid early
- Consider Acyclovir
- Give Dexamethasone with Antibiotics – it can reduce neurological sequelae
- Consider indications for CT before LP
- Get SENIOR support early
Category: Medical
HCID’s (High Consequence Infection Diseases)
High Consequence Infectious Diseases (HCIDs) include a group of rare but severe infections that require
ACTIONS – CARD HERE
- Immediate isolation
- Enhanced PPE
- Early specialist involvement.
Sickle Cell
Painful Crisis

Severe pain is the most common reason that patients with sickle cell, will attend the ED. The pain can be agonising (and often underestimated by us), we need to act fast to help ease the symptoms
Read moreRabies [notifiable disease]
Recent Incident: Bat contact was not recognised (effectively touching a bat without gloves means treatment is recommended)
Important: Rabies Vaccine is in short supply and we must do a UKHSA risk assessment. Call RIgS 09:30-17:00 7 days, Info required HERE

Rabies is an acute viral encephalomyelitis caused by members of the lyssavirus genus. The UK has been declared “Rabies-Free”. However, it is known that even in “Rabies-Free” counties the bat population posse a risk.
In the UK the only bat to carry rabies is the Daubenton’s Bat [Picture on the Left] and this is not a common bat in the UK. The UK and Ireland are Classified as “low-risk” for bat exposure. Despite our “low-risk” status in 2002 a man died from rabies caught in the UK from bat exposure.
Although rabies is rare it is fatal so we must treat appropriately, Public Health England – Green book details this.
Risk Assessment
To establish patients risk and thus treatment you need to establish the Exposure Category and Country Risk [Link to Country Risk]
Exposure Category

Combined Country/Animal & Exposure Risk
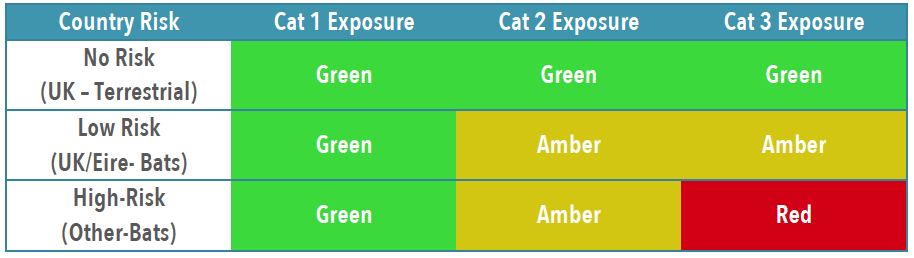
Treatment
Obviously patients with wounds will need appropriate wound care and cleaning, specifics for rabies are below.
If in ANY doubt, or you feel you need advice about treatment contact: On-Call Microbiologist (who will contact PHE or Virology advice)

You will likely need to liaise with the duty pharmacist to obtain vaccine or HRIG – which may need to be sent from a different hospital. [it is probably worth trying to obtain the 1st weeks treatment if possible, to avoid treatment delays]
IN HOURS 08:30AM-5PM PLEASE CALL PHARMACY TO INFORM THEM TO EXPECT A DELIVERY OF IMMUNOGLOBULIN SO THIS CAN BE SEGREGATED FOR THE CORRECT PATIENT. PLEASE ASK TO SPEAK TO THE RESPONSIBLE PHARMACIST CRH (4218/4279) HRI (2422/7123)
Rabies and Immunoglobulin Service (RIgS), National Infection Service, Public Health England, Colindale
- RIgS telephone number: 0330 128 1020.
- RIgS operates 7 days per week (9:30am to 5pm).
- The emergency out of hours service is only able to deal with calls about potential human cases of botulism or diphtheria, or the highest risk rabies exposures who have not already received one post-exposure dose of rabies vaccine (these are exposures to the head or neck, excluding those related to UK bats, or to an animal that is confirmed to have rabies).
- Health professionals calling about any other rabies exposures should administer a dose of rabies vaccine if the patient has not yet received any rabies vaccine (or if the next scheduled dose is due) and vaccine is available locally, and call back the next day after 9:30am to complete the risk assessment and confirm the timings for further vaccine doses.
- Information required – HERE
Notifiable Diseases
Registered Medical Practitioners in England and Wales have a statutory duty to notify Public Health about the following diseases. To facilitate rapid treatment and control of outbreaks. (Links to Wikipedia for illustrative purposes) Read more
Metastatic Spinal Cord Compression (MSCC)
This is guide to the investigation of Metastatic Spinal Cord Compression (MSCC) in Oncology/Haematology patients. – (Trust link)
You need to be a bit more suspicious and have a lower threshold for investigation than in patients without Known, Suspected OR Previous Malignancy Read more
Medical Emergencies in Eating Disorders
Eating disorders* are relatively common and unfortunately patients who “look well” can have a significant mortality risk. MEED.org.uk have national risk tools to recognise those that would benefit from admission, which fit with our local mental health teams, and agreed by both acute medicine and paediatrics
(*anorexia nervosa, bulimia nervosa, binge eating or avoidant restrictive food intake disorder)
Risk Assessment
RED indicators
Anyone with one or more RED’s is high risk and should be considered for admission MEED
- BMI <13/<70% mBMI
- Recent weight loss >1 kg/week for 2 weeks in an underweight patient
- HR (awake) <40
- Recurrent syncope with standing BP <90 systolic (<0.4th percentile for age) and postural drop >20 mmHg (or increase HR >30 [>35 if <16])
- Fluid refusal or signs of dehydration
- Temperature <35.5°C tympanic/35°C axillary
- Long Qt or other ECG abnormalities
- Low Glu/Na/K/Ca/PO4/Alb
- Low WCC, Hb <10
- Acute food refusal/very low calorie intake per day
- Physical struggles with carers over nutrition
- High levels of uncontrolled exercise (>2 hours/day)
- Daily purging behaviours
- Self-harm
- Moderate–high risk suicidal ideas.

Button Battery Ingestion
Oesophageal Button Battery = Emergency Refer Immediately
If anybody is symptomatic after button battery ingestion they need referral to the Surgical team for urgent endoscopic removal. Liase immediately with our local surgical/ENT teams but be aware this may end up as a time critical transfer to Leeds especially if child <2years. Read more
SNAP (paracetamol toxicity)

Rashes on Black & Brown Skin
Mind the Gap is a handbook of clinical signs in black and brown skins
Another excellent resource, especially for childhood rashes is the website SKINDEEP.

